

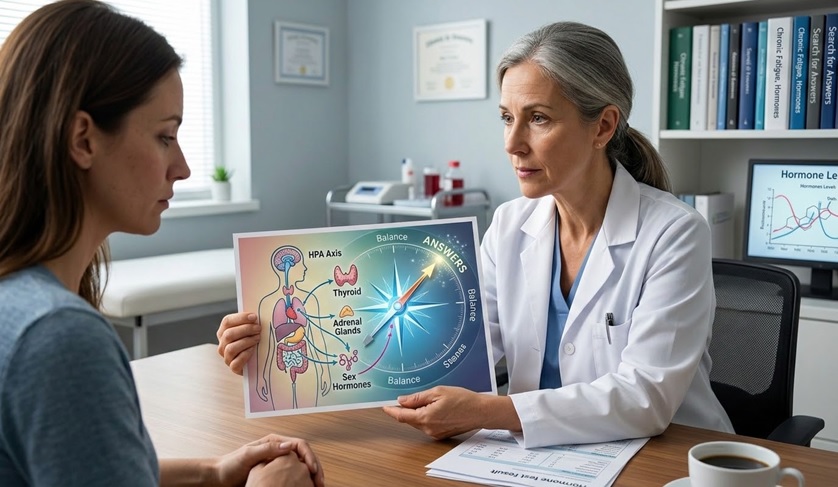
Persistent fatigue is one of the most frustrating symptoms in medicine because it can feel both vague and deeply disruptive. For many people, it is far more than ordinary tiredness. It can show up as heavy limbs, brain fog, poor recovery after activity, trouble concentrating, unrefreshing sleep, or the feeling that the body no longer responds the way it once did. Some people can point to when it started, often after an illness, a stressful life event, or a major shift in health. Others notice it building gradually, until everyday tasks begin to take far more effort than they should.
Part of the difficulty is that chronic fatigue rarely points to one clear explanation. Hormonal shifts can play a role, but so can insulin resistance, sleep disorders, nutrient deficiencies, autoimmune disease, neurological conditions, medication effects, depression, and post-viral syndromes. Sometimes several of these issues overlap. That is why finding answers often takes patience, thoughtful testing, and a willingness to look beyond a single body system.
Why Fatigue Is So Hard to Define
Fatigue is not a diagnosis. It is a symptom with many possible causes, and people describe it in very different ways. One person may say they feel drained all day. Another may say they crash after minimal activity. A third may notice mental exhaustion more than physical weakness. Those differences matter because they can point clinicians in very different directions.
A useful evaluation starts by separating fatigue from related complaints like sleepiness, shortness of breath, low motivation, muscle weakness, and exercise intolerance. Someone who feels drowsy may need a sleep assessment. Someone who becomes shaky and irritable after meals may need metabolic testing. Someone who gets much worse after exertion may need closer evaluation for post-exertional illness. The more clearly fatigue is described, the more likely testing will be targeted and useful.
Hormones and the Body’s Energy Balance
Hormones help regulate energy production, temperature, sleep, appetite, mood, and recovery. When they are out of balance, the body can feel as though it is running below capacity. Thyroid dysfunction is a common example. Too little thyroid hormone can slow metabolism and contribute to fatigue, constipation, weight gain, and cognitive slowing. Cortisol problems, changes in estrogen and progesterone, and low testosterone can also affect stamina and mental clarity.
Because hormonal symptoms overlap with so many other conditions, a careful review matters more than assumptions. Blood work may include thyroid studies, blood sugar markers, vitamin levels, and sex hormone testing when it makes clinical sense. In some cases, clinicians may also look at symptoms across the menstrual cycle, changes during perimenopause or menopause, or age-related shifts in testosterone. The goal is not to treat lab values in isolation, but to understand whether a hormonal pattern fits the person’s full clinical picture.
When Hormonal Care Becomes Part of the Plan
For some patients, fatigue is tied in part to symptoms of hormone imbalance, such as sleep disruption, low libido, mood changes, weight shifts, or reduced resilience under stress. In those cases, physician-guided treatment may involve lifestyle changes, monitoring, and sometimes hormone therapy. Clinics such as PhySlim focus on bioidentical hormone replacement therapy, including personalized BHRT planning designed to match treatment to an individual’s symptoms, history, and lab findings.
That kind of approach can be helpful when it is framed the right way, as one possible part of care, not a universal answer to every case of fatigue. Hormone treatment tends to work best when it sits inside a broader medical evaluation that also considers cardiovascular risk, metabolic health, sleep quality, and medication interactions. Even when hormones do play a role, follow-up matters because dose, symptom response, and side effects all need ongoing review.
Metabolic Health, Blood Sugar, and Daily Energy
Metabolic problems often develop slowly, which is one reason they are easy to miss. A person may not realize that rising blood sugar, insulin resistance, or increased visceral fat is affecting energy until fatigue becomes persistent. Some people notice post-meal sluggishness, afternoon crashes, or a cycle of cravings and low energy that worsens over time. Others develop poor sleep, weight gain, and inflammation that further reduce stamina.
Basic screening can reveal important clues. A complete blood count may show anemia. A metabolic panel can identify kidney or liver issues. Hemoglobin A1c, fasting glucose, and lipid markers can point to insulin resistance or early metabolic dysfunction. These results do not explain every case of chronic fatigue, but they often uncover patterns that can improve through nutrition, sleep support, exercise pacing, and, when appropriate, medical treatment.
Fatigue in Men’s Health and Midlife Change
In men, fatigue is sometimes linked to a broader cluster of symptoms that includes loss of muscle mass, low motivation, depressed mood, reduced sexual function, and weight gain. Testosterone is only one part of that picture, but it can be an important one. Low testosterone can overlap with sleep apnea, insulin resistance, chronic stress, and depression, which means evaluation should not stop with a single lab result.
A clinic such as EveresT Men’s Health may come into the conversation when a patient needs a focused assessment for low testosterone treatment or medical weight loss. In a careful setting, testosterone therapy is considered alongside body composition, cardiovascular risk, fertility goals, and long-term monitoring. That matters because fatigue in men is rarely solved by one intervention alone. Hormonal treatment may help some patients, but only when paired with a broader look at sleep, exercise tolerance, diet, and underlying medical conditions.
Neurological Conditions and the Problem of “Invisible” Illness
Not all fatigue begins in the endocrine or metabolic systems. Neurological conditions can change how the brain and body handle effort, stress, and sensory input. Multiple sclerosis, migraine disorders, dysautonomia, small fiber neuropathy, post-concussion syndromes, and other neurological problems can all produce profound fatigue. In many cases, people also experience dizziness, headaches, memory trouble, light sensitivity, or difficulty tolerating standing and exertion.
These illnesses can be hard to recognize because standard tests may look normal early on, or symptoms may fluctuate from day to day. That does not make them any less real. It simply means the diagnostic process may require a more detailed neurological exam, imaging, autonomic testing, or specialist referral. Listening closely to the pattern of symptoms, especially what makes them worse and what brings relief, can be just as important as any single lab result.
Post-Exertional Illness and Why Pushing Through Can Backfire
One of the most misunderstood forms of chronic fatigue is post-exertional malaise, often described as a worsening of symptoms after physical, cognitive, or emotional effort. This is not the same as feeling tired after a workout or a long day. The hallmark is a delayed and disproportionate symptom flare, sometimes appearing hours later and lasting for days or longer. People may experience crushing exhaustion, pain, cognitive decline, flu-like symptoms, or reduced function after an activity that once felt manageable.
This pattern is seen in conditions such as ME/CFS and in some people with post-viral illness. It changes the treatment logic completely. Standard advice to gradually push harder can make symptoms worse when the underlying problem is impaired recovery from exertion. In those cases, pacing, energy conservation, and individualized activity limits are often safer than generic exercise recommendations. Recognizing that distinction can prevent serious setbacks and give patients language for what they have been experiencing.
Testing That Helps Document Exertion Intolerance
Because post-exertional symptoms can be difficult to measure with routine office testing, more specialized assessment may sometimes be needed. The Workwell Foundation is known for 2-Day CPET testing, which has been used to document post-exertional malaise and changes in function across repeated exertion. In the right clinical context, this type of evaluation can help show that symptom worsening is physiological, rather than simply a matter of deconditioning or poor effort.
Even so, that kind of testing is not right for everyone, especially if exertion itself carries a risk of prolonged relapse. Decisions about advanced testing should weigh the value of documentation against the burden on the patient. In practice, the larger lesson is that exertion intolerance is real, measurable in some settings, and important to distinguish from ordinary fatigue. That distinction can shape disability documentation, treatment planning, and daily life management.
The Value of Broad Screening and Primary Care Coordination
Even when fatigue seems highly specific, a broad medical screen is often the best place to begin. Primary care can help rule out common but important contributors such as anemia, thyroid disease, uncontrolled diabetes, infection, medication side effects, kidney problems, liver disease, and inflammatory conditions. It also creates a baseline from which referrals can be made more efficiently.
This is where practices such as Internal Medicine & Primary Care of Sebastian fit into the larger picture. Chronic disease evaluation and primary care screening can help organize the first phase of investigation, especially for patients whose symptoms touch multiple systems. A coordinated primary care approach does not replace specialty care, but it often prevents fragmented treatment by making sure the major possibilities are assessed in a logical order.
Why Multidisciplinary Care Often Works Best
Persistent fatigue tends to resist simple explanations because the body’s systems do not operate independently. Sleep affects hormones. Hormones affect metabolism. Metabolic health influences inflammation. Neurological stress can alter heart rate, blood pressure, and cognitive endurance. A patient may also be coping with chronic pain, anxiety about lost function, or the practical toll of not being believed. All of that can magnify symptoms without making them imaginary.
That is why multidisciplinary care is often more effective than chasing a single fix. A person may need primary care testing, endocrine review, nutritional support, sleep evaluation, mental health care, and physical rehabilitation tailored to their tolerance level. In some cases, symptom management and functional adaptation become just as important as finding a neat label. The goal is not only to identify disease, but to improve daily life in realistic, sustainable ways.
Conclusion
Chronic fatigue can be a long and uneven journey, especially when symptoms cross the boundaries of traditional medical specialties. Hormonal imbalance may be part of the story, but so can metabolic dysfunction, neurological illness, sleep disruption, chronic disease, or post-exertional syndromes. The search for answers becomes more productive when fatigue is treated as a serious clinical signal, not a vague complaint.
A careful path forward usually starts with a clear description, solid screening, and an openness to more than one explanation at a time. For many patients, improvement comes not from one dramatic breakthrough, but from connecting the right pieces: better testing, smarter pacing, more precise treatment, and a care team willing to look at the whole person.